Search by Blog
Read by Category

Your healing journey continues beyond this blog

Find the right products for better recovery at online store
Cart Image
Poor posture while sitting causing back pain

Back pain rarely comes from one dramatic moment. More often, it builds slowly — from how you sit, how you lift, and how much you move (or don’t) during an ordinary day.

The good news: because these habits are small and repeated, small corrections add up fast. Here are the five biggest everyday culprits, and what to actually do about each one.

1. Poor Posture During Screen Time

Slouching while looking at a screen pulls your head forward and loads your spine with extra weight it wasn’t built to carry in that position — over hours, this causes fatigue, stiffness, and pain.

Fix it:

  • Sit with your spine neutral and shoulders relaxed, not hunched forward
  • Raise screens to eye level so you’re not bending your neck down
  • Use an ergonomic chair or a lumbar support cushion
  • Stand or stretch every 30–45 minutes
If you're managing an existing strain or a support during long desk hours, a soft posture corrector can help retrain alignment. For a deeper look at why this matters beyond just back pain, see the health benefits of good posture.

2. Incorrect Lifting Techniques

Bending at the waist to lift — instead of bending your knees — puts sudden, concentrated pressure on your lower back. Do this repeatedly and you risk a genuine muscle strain, not just soreness.

Fix it:

  • Bend your knees, not your back
  • Keep the object close to your body
  • Keep your back straight through the lift
  • Never twist your torso while carrying weight
If a strain has already happened, our guide on muscle strain causes and recovery covers what actually supports healing — and what can slow it down. Muscle strains are also common in athletes, particularly in sports involving sprinting, jumping, kicking, and other explosive movements. For a broader look at sports-related orthopedic injuries, see our guide on orthopedic injuries in athletes.

3. Sitting for Long Periods Without Movement

Long, unbroken sitting stiffens the back and hips and slows circulation — and reduced blood flow means more muscle fatigue and discomfort, even without any single “wrong” movement.

Fix it:

  • Stand or walk for a few minutes every hour
  • Add simple back and leg stretches through the day
  • Use a standing desk if it’s available to you

Circulation-focused support can also help here. Compression bandages are sometimes used to support circulation during long periods of inactivity, particularly for the legs.

4. Weak Core Muscles

Your abdominal and lower-back muscles share the job of stabilizing your spine. When they’re weak, your spine has to work harder on its own — and that imbalance shows up as fatigue and pain over time.

Fix it — simple strengthening moves:

  • Bridges
  • Planks
  • Pelvic tilts
These don't need to be intense. Consistency matters more than difficulty here.

5. Lifestyle Factors That Strain the Spine

Extra body weight, an unsupportive mattress, and chronic stress all add ongoing load to your spine — none of these show up as a single injury, but together they compound.

Fix it:

  • Maintain a healthy body weight
  • Choose a mattress that supports spinal alignment
  • Build in relaxation techniques to ease muscle tension
If back pain has become a longer-term, ongoing issue rather than an occasional twinge, our guide on the role of exercise in chronic pain management covers how movement, not prolonged rest, can be part of a better long-term strategy. 

A physiotherapist can also assess what’s contributing to your pain and help you build an exercise and recovery plan suited to your needs. For lower back-specific support, a lumbo-sacral support may provide additional support during certain activities or periods of recovery.

When Back Pain Needs Medical Attention

Occasional discomfort that improves with posture changes and movement is common and usually not serious. See a doctor if:

  • Pain becomes severe or persistent
  • Movement becomes noticeably difficult
  • Pain spreads down into your legs or elsewhere
A healthcare professional can properly evaluate the cause and recommend the right treatment or rehab plan — self-managing is fine for mild, short-term discomfort, but not for these signs.

Supporting a Healthier Back

Most back pain isn’t caused by one bad moment — it’s built from small daily habits. Fixing your posture, lifting correctly, moving more, and strengthening your core will do more for your spine than almost anything else. For extra support during recovery or long days, browse the full orthopaedic products range.

Related reading:

Visit www.dattmedi.com for more infomation.
Share:

Frequnently Asked Questions

Yes. Poor posture places ongoing strain on the muscles and joints supporting the spine, leading to discomfort and fatigue over time.

Standing or moving every 30–60 minutes helps maintain circulation and reduce stiffness.

Bridges, planks, and pelvic tilts are simple, effective moves that build the muscles supporting your spine.

Yes. Lifting with a bent back instead of bent knees increases spinal pressure and raises injury risk.

If pain is severe, persistent, or comes with limited movement or other unusual symptoms, get it checked rather than waiting it out.

Recent Blogs
Knee brace and compression sleeve comparison

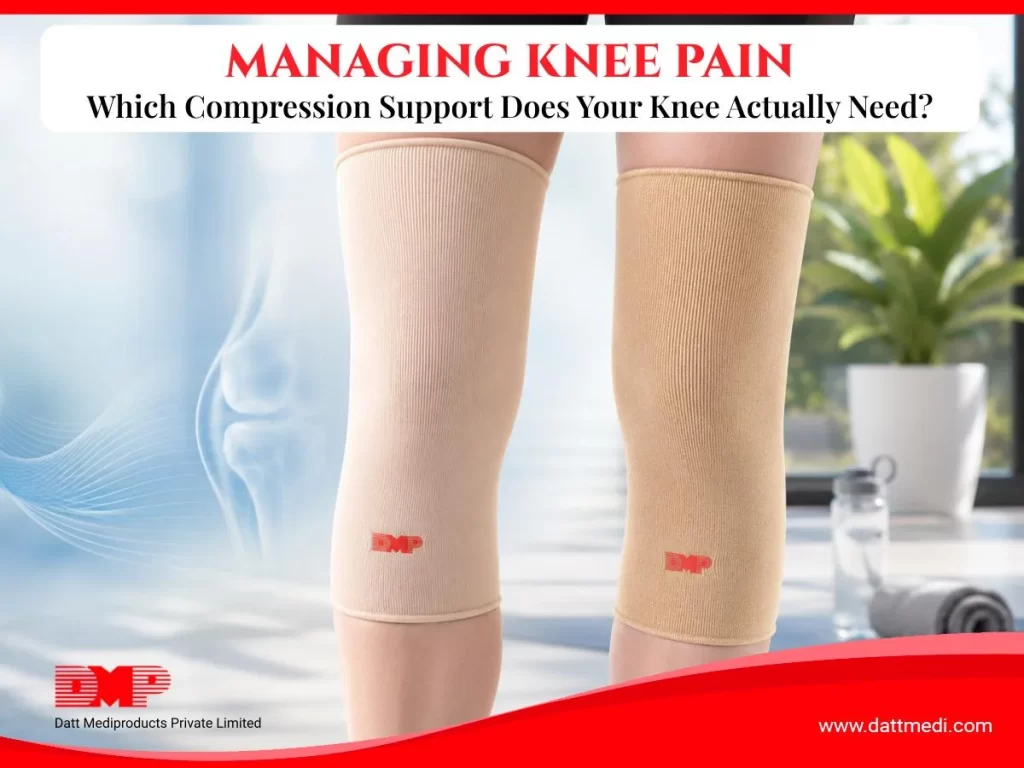
Knee compression supports are one of the most commonly used orthopedic aids — for good reason. They reduce swelling, provide joint stability, and allow people to stay active during recovery. But picking the wrong one delivers less benefit than it should.

The Datt Mediproducts range includes two knee compression supports: the Knee Cap® and the Knee Cap Classic®. Both share the same anatomically tapered form and four-way elasticized construction, but differ in material composition — and that difference matters for fit, stretch, and the conditions each handles best.

This guide breaks down both products clearly so you can match the right support to the right situation.

Understanding Knee Compression Supports

Before comparing the two products, it helps to understand what knee compression supports actually do — and what they don’t.

A compression sleeve works by applying graduated pressure around the knee joint. This pressure does three things: it reduces fluid accumulation in the surrounding tissue (reducing swelling), it improves preconception — the joint’s sense of its own position in space — which improves stability and coordination, and it provides mild structural support to the muscles and ligaments surrounding the joint.

Compression sleeves are not rigid braces. They do not prevent movement or immobilize the joint. Their role is to support the knee while allowing full, natural range of motion — making them suitable for both active use during daily activity and recovery phases where movement is encouraged.

Knee Cap® vs Knee Cap Classic®: What Is Actually Different?

Both products share the same core design: anatomically tapered, four-way elasticized fabric, breathable moisture-transporting weave, beige color, and easy pull-on application. Available in S to XXL (37–67 cm thigh circumference). The key difference is material composition.

FeatureKnee Cap®Knee Cap Classic®
MaterialPolyamide, Polyester, Cotton, Nylon, Spandex, RubberPolyamide, Polyester, Cotton, Rubber
Key differentiatorContains Spandex + Nylon — higher elasticity and stretch recoveryNo Spandex — firmer, more structured fabric
Compression feelSofter, more flexible compression — moves freely with the jointFirmer, more structured compression — greater sense of support
Best forActive use, exercise, long-duration wear, mild-to-moderate conditionsRecovery, post-operative support, instability, conditions needing firmer hold
IndicationsArthritis, swelling, sprains, ligament/muscle injury, post-op, weak kneesArthritis, swelling, sprains, ligament/muscle injury, post-op, weak knees
SizesS, M, L, XL, XXLS, M, L, XL, XXL
ColourBeigeBeige

Knee Cap® — When to Choose It

The inclusion of Spandex and Nylon gives the Knee Cap® a higher degree of stretch and elastic recovery. The fabric moves with the joint rather than resisting it, making it more comfortable for extended wear and higher-activity use.

Best suited to:

  • Daily activity support — long hours of standing, walking, or commuting
  • Exercise and sports — where full range of motion is needed alongside compression
  • Mild-to-moderate swelling from arthritis or overuse
  • Sprains and strains in active recovery, where movement is encouraged
  • Individuals who have worn a rigid brace and are transitioning to lighter support
  • Long-duration wear where breath-ability and comfort are priorities

The four-way stretch and moisture-transporting weave make it particularly well-suited to warmer climates or extended wear through a full workday.

Knee Cap Classic® — When to Choose It

Without Spandex, the Knee Cap Classic® fabric is slightly firmer and provides a more structured feel against the joint. For some users — particularly those managing instability or recovering from injury — this firmer hold provides greater confidence during movement.

Best suited to:

  • Post-operative knee support — where firmer compression is preferred in the early recovery phase
  • Ligament injuries — where the joint needs a stronger sense of containment
  • Knee instability — where proprioceptive feedback from firmer compression helps prevent giving way
  • Arthritic pain management — particularly where the joint feels loose or unpredictable
  • Individuals who find softer sleeves feel insufficient for their level of discomfort
The Classic’s firmer structure makes it the better starting point when someone is first introducing compression support and needs the reassurance of a more defined hold.

Clinical Indications: Both Products

Both the Knee Cap® and Knee Cap Classic® are indicated for the same range of conditions. The choice between them is about compression feel and activity level, not about which conditions they cover.

  • Arthritic knee pain — reduces swelling and improves joint comfort during movement
  • Swelling from injury or post-operative recovery — graduated compression reduces fluid accumulation
  • Ligament and muscle injuries — supports the surrounding soft tissue during healing
  • Sprains and strains — protects the joint during active recovery
  • stabilization of weak knees — improves preconception and confidence during weight-bearing
  • Post-operative knee support — provides compression during the rehabilitation phase

How to Size Correctly

Both products are sized by thigh circumference, measured approximately 15 cm above the center of the kneecap. An incorrect size is one of the most common reasons compression sleeves under perform — too loose provides minimal compression; too tight restricts circulation.

SizeInchesCentimetres
S14.8 – 17.2″37 – 43 cm
M17.2 – 19.6″43 – 49 cm
L19.6 – 22″49 – 55 cm
XL22 – 24.4″55 – 61 cm
XXL24.4 – 26.8″61 – 67 cm

Safe Use Guidelines

When to Wear It

Compression sleeves are designed for use during periods of activity and weight-bearing — standing, walking, exercising. Most people do not need to wear them at night or during extended rest periods. If your clinician has advised otherwise, follow their specific guidance.

Combining with Rehabilitation

Compression support works alongside rehabilitation — not instead of it. Quadriceps strengthening, hamstring flexibility, and hip stability exercises address the underlying muscle weakness that contributes to knee instability and pain. A compression sleeve manages symptoms during activity; exercise addresses the cause.

Signs the Fit Needs Adjusting

  • Sleeve rolls down or bunches behind the knee — size may be too large
  • Visible skin bulging above or below the sleeve — size may be too small
  • Numbness, tingling, or increased swelling below the knee — too tight, remove immediately
  • No perceptible compression when standing — fabric has lost elasticity, replace the sleeve
Managing Orthopedic Injuries

Related reading: From the Field to Recovery: Orthopedic Injury Essentials for Athletes

When Compression Is Not Enough

Compression sleeves are appropriate for a wide range of common knee conditions. However, some situations require more rigid structural support than a sleeve can provide:

  • Significant ligament instability (ACL, PCL, MCL, LCL tears) — typically requires a hinged brace
  • Meniscal injuries with mechanical symptoms (locking, giving way) — requires clinical assessment
  • Post-operative immobilisation immediately after surgery — rigid brace or cast typically prescribed
  • Fractures or bone stress injuries — require immobilisation, not compression
If you are unsure which level of support your condition requires, consult a physiotherapist or orthopedic specialist before selecting a product.

Choosing the Right Support from the Start

The difference between the Knee Cap® and Knee Cap Classic® comes down to how the compression feels against the joint and what activity level the sleeve needs to accommodate. For flexible, active, long-duration use — the Knee Cap®. For a firmer, more structured hold during recovery or instability — the Knee Cap Classic®.

Both are sized S to XXL, both are breathable and pull-on, and both cover the full range of common knee conditions. The right one is the one that matches how your knee feels and what you need it to do.

Browse: Knee Cap®  |  Knee Cap Classic®

Understanding Arthritis

Related reading: The Role of Orthopedic Support Products in Arthritis Pain Management

Muscle stiffness after prolonged immobilization with cast

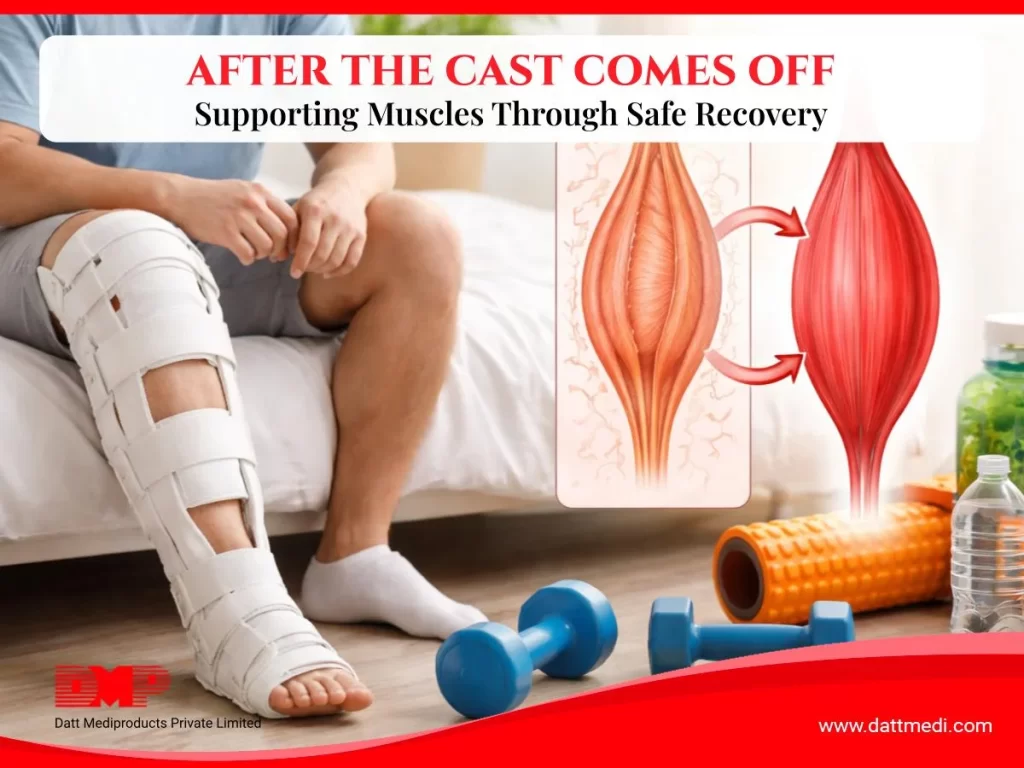
Coming out of a cast, brace, or splint is rarely as straightforward as it looks. The injury may have healed, but the surrounding muscles, joints, and soft tissue have spent weeks in a fixed position with limited activity. What follows is not a return to normal — it is the beginning of a second phase of recovery that requires just as much attention as the first.

This guide covers what actually happens to muscles and joints during immobilization, how to rebuild strength and mobility safely, and which specific orthopedic supports help — matched by body part and stage of recovery.

What immobilization Does to the Body

Muscle reconditioning

Muscles maintain their strength through regular contraction. When a limb is immobilized, the muscles around it stop receiving the mechanical signals they need to stay strong. The result is a measurable loss of muscle mass and endurance — a process called disuse atrophy. Studies show that muscle strength can decline by as much as 3–5% per day in the early stages of immobilization. Even a three-week cast can produce noticeable weakness in the surrounding musculature.

Joint Stiffness and Reduced Range of Motion

Joints rely on movement to stay healthy. Synovial fluid — the lubricant inside joints — circulates through movement. When a joint is held still for weeks, the surrounding capsule and ligaments begin to shorten and stiffen, and the range of motion decreases. Regaining that range requires deliberate, progressive movement — not just returning to normal activity.

Circulation and Swelling

immobilized limbs often develop swelling because the muscle pump that normally drives venous return is inactive. Fluid accumulates in the soft tissue, particularly around the ankle and foot in lower limb immobilization. This swelling can itself delay rehabilitation by limiting movement and causing discomfort.

The Four Phases of Returning to Movement

Phase 1: Protected Range of Motion

Immediately after immobilization ends, the goal is gentle, pain-free movement — not strength. Ankle circles, wrist rotations, finger flexion, and similar small movements reintroduce the joint to its range without stressing the recovering tissue. Movement should stay within a comfortable range and never push into pain.

Phase 2: Circulation and Swelling Control

Before strength can return, swelling needs to reduce. Elevation, gentle movement, and compression where appropriate help manage fluid accumulation. This phase often runs parallel to Phase 1.

Phase 3: Strength Rebuilding

Once range of motion is partly restored and swelling is controlled, progressive resistance exercises can begin. Resistance bands are useful here because they allow graded loading — starting light and increasing gradually without placing sudden stress on healing tissue. Physiotherapy guidance is strongly recommended for this phase.

Phase 4: Functional Reintegration

The final phase returns the person to normal activity — walking, lifting, working, exercising — progressively. Supportive bracing may continue during this phase to provide stability while the muscles are still rebuilding.

Why Muscle Strains Happen

Related reading: Understanding Muscle Strains: Causes and Effective Recovery Strategies

Nutrition That Supports Muscle and Bone Recovery

The body rebuilds muscle tissue and bone using raw materials from diet. The following nutrients are most directly relevant during post-immobilization recovery:

  • Protein — essential for muscle repair and rebuilding. Sources include eggs, legumes, dairy, fish, and lean meat. Aim for consistent intake across meals rather than one large serving.
  • Calcium — supports bone density and structural recovery, particularly relevant after fractures. Dairy products, fortified plant milks, and leafy greens are good sources.
  • Vitamin D — required for calcium absorption. Many people in India are deficient, particularly those with limited sun exposure. Supplementation is often advisable — check with a doctor.
  • Collagen precursors (Vitamin C, zinc) — support soft tissue and tendon repair. Found in citrus fruits, berries, nuts, and seeds.
  • Hydration — adequate water intake supports muscle function, joint lubrication, and circulation during rehabilitation.

Which orthopedic Support to Use — by Body Part and Stage

Supportive braces and sleeves serve two distinct roles during post-immobilization recovery: they protect the recovering joint from excessive or sudden movement, and they provide proprioceptive feedback — helping the nervous system re-learn where the joint is in space. The right product depends on which body part was immobilized and what stage of recovery the person is in.

Body PartRecovery StageRecommended ProductWhy It Helps
KneeEarly — swelling, weakness, instabilityKnee Cap®Firm compression reduces swelling; supports ligaments and muscles during initial movement
KneeLater — returning to activity, mild ongoing instabilityKnee Cap Classic®Lighter everyday support for stable knees still rebuilding strength during functional activity
Lower back / lumbarAny stage post-immobilisation or injuryLumbo Sacral Support®Stabilises the lumbar spine and reduces load on recovering muscles during standing and movement
Shoulder / arm / elbowEarly — immediately after cast or surgeryPouch Arm Sling®Positions the arm comfortably during early recovery; reduces load on shoulder and elbow joints
Neck / cervicalEarly — post-collar or post-surgeryCervical Collar SoftGentle support as neck muscles begin reactivating; acts as a movement reminder without full restriction
Neck / cervicalModerate — where more stability is neededCervical Collar Soft-Support®Firmer foam with reinforced support — suited to cases where more restriction is clinically indicated
Calf / lower legAny stage — venous or lymphatic involvementVelcare® Inelastic WrapInelastic compression supports venous return and reduces swelling when calf muscle pump is inactive or rebuilding
Foot / ankleAny stage — foot swelling or post-castVelcare® Medical StockingGraduated compression for the foot and ankle; particularly useful where swelling persists after lower limb immobilisation
Upper back / postureRehabilitation phase — relearning upright posturePosture Corrector®Supports spinal alignment and shoulder positioning as back and core muscles regain strength

Safe Guidelines for Early Movement

Always Get Clearance First

No exercise or movement programmed should begin without confirmation from the treating clinician or physiotherapist that it is safe to do so. The timeline varies significantly depending on the type of injury, the location, and how healing has progressed.

Start Smaller Than You Think You Need To

The instinct after weeks of immobilization is to move more to make up for lost time. This usually backfires. Muscles and tendons that have been inactive are more vulnerable to strain, and joint tissue is still adapting. Small, controlled movements performed consistently will restore strength faster than pushing into discomfort.

Pain Is a Signal, Not an Obstacle

Discomfort from stiffness is expected and normal. Sharp or worsening pain during exercise is not. If a movement causes significant pain, stop, and raise it with a healthcare professional before continuing.

Use Supports Correctly

A brace or support is most effective when sized and positioned correctly. An ill-fitting support — too loose or too tight — can create pressure points, restrict circulation, or provide false confidence that leads to overexertion. Follow sizing guidance for each product, and if in doubt, seek fitting advice.

When to See a Physiotherapist

Physiotherapy is not just for serious injuries. A physiotherapist can assess the specific degree of muscle weakness and joint restriction after immobilization, design a graduated programmed matched to the person’s actual capacity, and identify any complications — such as tendon tightness, abnormal movement patterns, or persistent swelling — that need addressing before progressing.

The Role of Compression Therapy

Related reading: Compression Therapy: A Key Trend in Modern Wellness Routines

Recovery Is a Process, Not an Event

The end of immobilization marks the beginning of rebuilding — not the end of recovery. Muscle reconditioning, joint stiffness, and residual swelling are normal consequences of keeping a limb still, and all of them respond well to progressive, consistent rehabilitation.

The right orthopedic support — matched to the body part, the stage of recovery, and the level of activity — makes that process safer and more manageable. Browse the full Datt Mediproducts orthopedic range to find the support that fits your recovery.

Logo

Datt Mediproducts Private Limited

Loading
Buy Now Contact Us